
CLINICAL MEMORY
Longitudinal Cycle Memory
Find 40+ REI prompt packs at templates.scribing.io to draft monitoring notes in seconds and surface unresolved follicular and endometrial questions.
Specialty Clinical Playbook
Convert cycle-day monitoring into traceable FHIR Observations with audit-ready billing evidence, not autonomous coding. Book your audit at https://cal.com/merryai/demo.
 Dr. Sarah Chen, MD
Specialty Architecture
Engineered to mirror the pacing, diagnostic frameworks, and documentation requirements of Reproductive Endo (REI).
CLINICAL MEMORY
Find 40+ REI prompt packs at templates.scribing.io to draft monitoring notes in seconds and surface unresolved follicular and endometrial questions.
CONTEXT RETRIEVAL
Retrieve prior estradiol, progesterone, and follicle-cohort trends across stimulation days in one structured draft without tab bouncing.
WORKFLOW INTELLIGENCE
Assemble longitudinal complexity evidence and auto-draft care plans for human review. Claim your 15-Minute Workflow Audit today.

SPECIALTY-AWARE REASONING
Diarize partner and intended-parent dialogue and map follicular, hormonal, and endometrial findings into REI-approved note sections.
Point-of-Care Flow
Zero IT friction, zero complex API setup, and human-verified attestation on every note.

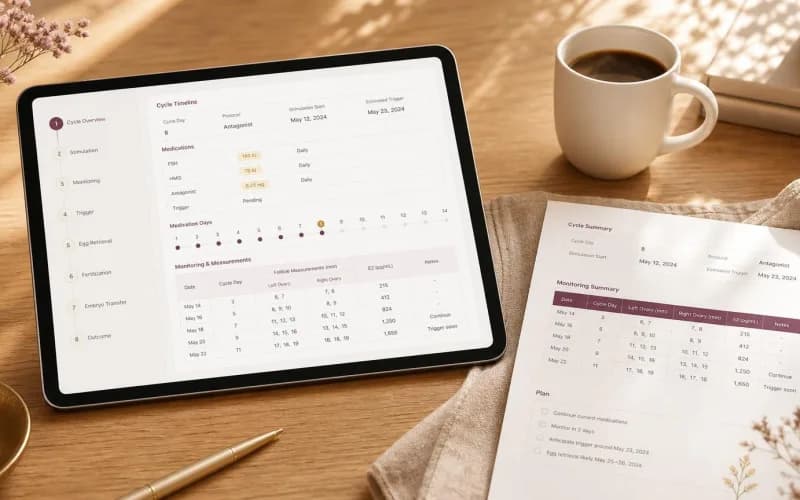
Clinical documentation in Reproductive Endocrinology demands the simultaneous orchestration of ultrasound morphometry, serum endocrinology, medication exposure, and cycle context into a single defensible record. A monitoring encounter is not a single data point but a convergence of transvaginal follicle measurements, endometrial thickness and pattern, estradiol and progesterone trajectories, gonadotropin dosing, and the physician's continuation-or-cancellation decision. Merry AI's anchor workflow maps each of these streams into standardized FHIR Observations while preserving the linkages back to the Encounter, ServiceRequest, Procedure, and cycle episode that make the data auditable.
The critical architectural principle is that a FHIR mapping does not, by itself, justify a claim. A value such as "estradiol 1,250 pg/mL" is evidence; "continue stimulation at 150 IU and repeat ultrasound in 48 hours because the follicular cohort is developing appropriately" is the Medical Decision Making that makes the evidence billable. Merry AI keeps these strictly separate, routing raw measurements into Observation resources and physician interpretation into structured assessment-and-plan documentation or a DiagnosticReport conclusion. This separation mirrors ASRM laboratory guidance on reliable result transmission and retrievable records.
Referential integrity remains the single most important interface requirement across the IVF EHR, embryology LIMS, laboratory information system, and ultrasound archive. Every imported result must be traceable to the patient, encounter, order, specimen or study, cycle, and source system. Patient and cycle identity should never depend on free-text names alone, because gametes, embryos, and donor material may be associated with multiple individuals and legal entities requiring stronger identity controls than ordinary outpatient documentation.
The following matrix demonstrates how REI diagnostic frameworks translate into required clinical data points and the corresponding billing defense. Each row reflects the chain from encounter through interpretation to payer-defensible evidence, not an automated code determination.
| Specialty Diagnostic Framework | Required Clinical Data Points | Billing Evidence |
|---|---|---|
| Ovarian Stimulation Monitoring | Follicle count per ovary, follicle dimensions (mm), stimulation day, gonadotropin dose | Medical necessity for serial E/M; longitudinal cycle complexity supporting G2211 |
| Endometrial Adequacy Assessment | Endometrial thickness, trilaminar pattern, transfer-readiness timestamp | Ultrasound interpretation evidence; documented MDM for transfer scheduling |
| Hormonal Response Interpretation | Estradiol, progesterone, LH, hCG values with LOINC codes, UCUM units, reference ranges | Separately reportable laboratory interpretation; premature LH surge risk documentation |
| Hyper-Response / OHSS Risk Stratification | Total follicle cohort >18-20, peak estradiol, prior cycle history | Complexity of MDM justifying higher E/M level with human review |
| Cycle Cancellation / Trigger Decision | Continuation status, trigger medication and timing, next-event scheduling | Documented clinician decision and patient communication for claim linkage |
Every monitoring event must capture at least two patient identifiers, the stable cycle identifier, cycle day and stimulation day, the ordering clinician, the tests ordered, specimen type with collection date-time and accession number, the sonographer and equipment identifier, and the medication dose at the moment of monitoring. Cycle day should be represented as structured data, not merely a phrase in a note, including calendar date, cycle day number, stimulation day number, protocol phase, and whether the date was confirmed or estimated.
Each individual Observation retains a standardized LOINC code for laboratory analytes, value and UCUM unit, reference range, effective and issued timestamps, specimen information, performer, interpreting clinician, and status such as preliminary, final, amended, or corrected. Follicle measurements are generally represented as a separate observation per follicle or per clinically meaningful aggregate, with ovary laterality, follicle sequence, measurement plane, size, sonographer, and image linkage where available. A summary like "right ovary: six follicles 12-16 mm" is clinically useful but should never replace the underlying measurements when those measurements drive the treatment decision.
Results arrive from heterogeneous sources including in-house analyzers, reference laboratories, ultrasound machines, imaging systems, nursing documentation, and patient-entered medication logs. The ingestion layer supports HL7 v2 and FHIR interfaces, interface acknowledgment and retry handling, unit normalization, duplicate detection, and explicit separation of collected, performed, resulted, verified, and reviewed timestamps. Corrected reports must be issued promptly while retaining both the original and corrected versions, consistent with peer-reviewed guidance on real-time IVF data recording indexed at the National Library of Medicine.
Normalization should never erase the source value. The system retains the original result, original unit, normalized value, normalized unit, conversion method, source laboratory, mapping version, and mapping reviewer approval status. This matters acutely because fertility hormones vary by assay, unit, laboratory, and reference range; automated conversion without preserved source context can create clinically misleading records. Terminology governance spans LOINC, UCUM, SNOMED CT, ICD-10-CM, and CPT/HCPCS with versioned releases. Specialty prompt packs calibrated to these frameworks are available at Access Specialty Prompts at templates.scribing.io.
The phrase complex fertility billing is not a universal billing category. It may reference a complex E/M service, physician management of an active treatment cycle, separate ultrasound or laboratory services, bundled IVF packages, or payer-specific infertility benefits. Merry AI therefore positions its output as documentation support and coding-evidence assembly, never as an autonomous determination that a complex claim is justified. The coding engine remains architecturally separate from the clinical interpretation engine and applies current CPT, HCPCS, ICD-10-CM, and payer rules with human review for ambiguous claims.
FHIR Observations can prove that relevant data existed, that results were associated with the correct patient and cycle, that results were available at the time of decision-making, and can reconstruct the sequence of monitoring and treatment changes. They cannot, by themselves, prove that a physician personally performed or interpreted the service, that the service was medically necessary, that the payer covers it, that documentation satisfies a particular E/M level, or that a global IVF package does not already include the service. Per CMS guidance, G2211 reflects visit complexity inherent to continuing focal-point care, which an active cycle can genuinely represent when properly documented.
For every billed monitoring event the system reconstructs the patient and cycle, the order and ordering clinician, the collection or ultrasound timestamp, the service performed, the raw result reference, the final result status, the reviewing clinician, the medical assessment, the treatment decision, the patient communication, the claim line and diagnosis linkage, any correction or late entry, the AI-generated content, and the human approval. This chain is exportable in both human-readable and machine-readable FHIR form. Ready to see it applied to your protocols? Schedule a 15-Minute Specialty Workflow Audit.
Merry AI implements read-only default access to source clinical systems, role-based write permissions, human approval before any change enters the legal medical record, confidence scores with reason codes, source links for every extracted fact, and suppression of unsupported inferences. The AI never silently overwrites a final laboratory result, changes a cycle date, converts a preliminary result to final, or infers physician interpretation from a nursing or automated entry. Explicit "unable to determine" states are surfaced rather than fabricated conclusions.
Regulatory posture reflects HIPAA Privacy, Security, and Breach Notification Rules, executed Business Associate Agreements, and heightened sensitivity around infertility diagnosis, genetic testing, donor identity, embryo disposition, and reproductive-health data governed by evolving state law. Where the organization performs human laboratory testing, CLIA classification applies; ASRM notes endocrine immunoassay laboratories are commonly moderate complexity, though a single high-complexity test can reclassify the entire laboratory. Records retention should follow federal, state, and local requirements or ten years beyond final specimen disposition, whichever is later. The safest product boundary is unambiguous: Merry AI converts cycle-day monitoring data into traceable, standardized clinical facts and assembles an audit-ready package for human review and payer-specific coding, with traceability as the core differentiator.

Convert dietetic assessments into clinician-reviewed ADIME drafts with transparent G0270 unit logic. Book your audit at https://cal.com/merryai/demo.

Convert member priorities and verified data into traceable, clinician-reviewed longitudinal summaries and care-goal records. Book your audit at https://cal.com/merryai/demo.

Structured GLP-1 documentation, BMI-indexed milestone tracking, and payer-ready prior-auth evidence built for metabolic medicine. Book your audit at https://cal.com/merryai/demo.